


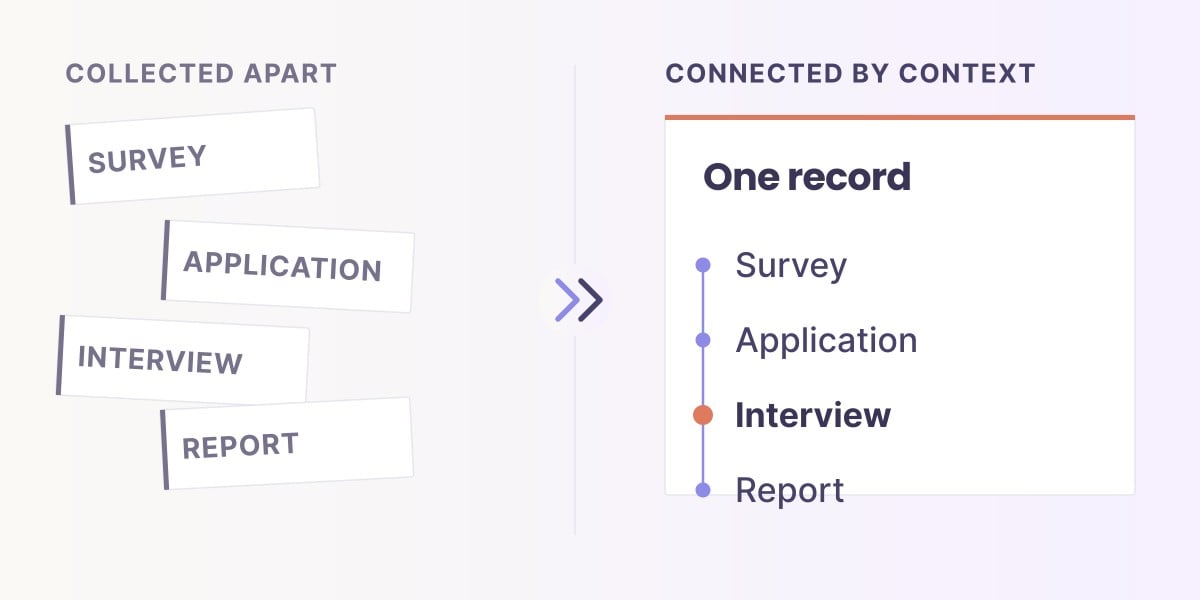
What is case management?
Case management is a collaborative practice that helps a person or family understand needs, agree goals, access appropriate services and review progress over time. It combines relationships, coordination, advocacy and documentation. The person receiving support is a participant in the work, not simply a record to be processed.
For example, someone entering a workforce program may need help navigating training, scheduling, transport and employer connections. A case manager works with the participant to understand priorities, agree a plan, coordinate support and revisit what is working. Recording those conversations helps the next interaction build on the previous one.
This guide explains the role, common stages, models, documentation and software. It also shows how to connect information across people and programs without treating an automated summary as a substitute for professional judgment.
What is the purpose of case management?
The purpose is to help people navigate support that can otherwise be fragmented. A referral, appointment or completed form is part of that work; it is not necessarily the result the person wants. The team needs to understand whether the support is accessible, useful and aligned with agreed goals.
The Case Management Society of America emphasizes collaboration in its explanation of the practice. In social work, the NASW standards address assessment, planning, coordination and evaluation alongside ethical responsibilities. The applicable role and requirements depend on the setting.
Good case management therefore asks more than “Has this task been completed?” It also asks what the person understands, what they prefer, what remains difficult and what the team can reasonably do next.
What does a case manager do?
Scroll horizontally to see all columns →
| Responsibility | Practical example | Useful record |
|---|---|---|
| Understand the situation | Discuss needs, strengths, preferences and existing support | Assessment with relevant context and the person's perspective |
| Agree goals | Choose a realistic next step with the participant | A plan showing responsibilities and review timing |
| Coordinate services | Arrange or follow up on an appropriate referral | The referral, status and relevant communication |
| Support access and advocacy | Clarify a process or help address an access barrier | The issue raised, action taken and unresolved needs |
| Review progress | Ask whether the support is working and adjust the plan | Updated evidence and the reason for a change |
| Support transition or closure | Agree next arrangements and document the ending of involvement | Closure or transfer reason, current status and next steps |
The role may be shared across a team. Clinical treatment, legal advice and other specialist services depend on the worker's qualifications and scope; the title “case manager” does not authorize every kind of intervention.
Where is case management used?
Case management appears in health and social services, housing support, disability services, workforce development, education and youth programs, reentry support and other settings where people need coordinated assistance. The vocabulary, professional responsibilities and record requirements vary.
A school-based support team may coordinate learning and family support. A workforce provider may connect training with employment services. A health team may coordinate care across providers. These examples share a need for continuity, but they should not be treated as one identical service model.
For a software decision, start with case management software. This article focuses on the practice that the software should support.
Six common stages of case management
The six stages below are a practical way to explain the work, not a mandatory sequence used identically in every sector. Assessment, planning, support and review often overlap or repeat. A transfer or closure can occur for several reasons, not only because every goal has been achieved.
Scroll horizontally to see all columns →
| Stage | What happens | Question to keep visible |
|---|---|---|
| 1. Intake and engagement | Establish contact, explain the service and collect relevant initial information | Does the person understand the purpose and next step? |
| 2. Assessment | Understand needs, strengths, context and available support | What matters to the person, and what needs further clarification? |
| 3. Planning | Agree goals, responsibilities and review timing | Is the plan meaningful and workable in this situation? |
| 4. Implementation and coordination | Deliver or arrange support and follow through on referrals | Was the support actually accessible and received? |
| 5. Monitoring and review | Examine progress and experience, then revise the plan where needed | What has changed, and what remains unresolved? |
| 6. Transition or closure | Document the reason involvement ends or transfers and the next arrangements | What continuity or follow-up is needed? |
A form completed at intake should not become a permanent description of a person. Later information may correct or expand it. Keep the source, date and review context of changes so the record supports learning rather than preserving an outdated label.
Continue to the case management process for a deeper walkthrough and case management workflow for operational steps.
Example: follow the support, not just the appointment
Fictional example. Alex joins a job-training program and wants to complete a qualification while continuing part-time work. At intake, Alex says evening sessions would be easier to attend. The initial plan includes training, an adviser check-in and an employer-information session.
After two missed appointments, a note records: “Alex reports that childcare was unavailable for the scheduled sessions and asks whether an evening option exists.” A useful next step is to discuss options and update the plan with Alex. The note does not justify describing Alex as unmotivated, diagnosing a condition or automatically raising a risk score.
Scroll horizontally to see all columns →
| What the record contains | What it supports | What it does not establish |
|---|---|---|
| Two missed appointments | A question about attendance and access | The reason for every missed contact |
| Alex's explanation about childcare | A reported barrier to discuss and act on | A verified explanation for everyone in the program |
| A revised evening-session plan | A documented response with an owner | Proof that the barrier has been resolved |
| Later participation and feedback | Evidence for the next review | Proof that one action caused every later outcome |
If another worker takes over, they should be able to see the current plan, the basis for it and the pending follow-up. Alex should not have to reconstruct the same history solely because the team changed.
Common approaches and models
Model names describe different approaches to delivering support. They are not interchangeable software settings or a single ladder of intensity. Programs should select and implement an approach using the relevant professional guidance, population needs, staffing and service resources.
- Brokerage-oriented work emphasizes connecting people with appropriate services and following up on those connections.
- Strengths-based practice centers the person's capacities, preferences and resources alongside needs. It can inform different service arrangements.
- Clinical case management may combine coordination with clinical work within the practitioner's qualified role.
- Intensive case management involves a higher level of support and contact appropriate to its setting; it requires the corresponding resources and practice design.
Assertive Community Treatment is a specific multidisciplinary, community-based service model, not simply another name for any high-intensity caseload. SAMHSA's ACT resources explain that model. Its specialized requirements should not be inferred from a general case-management guide.
A software system can support records and coordination within a model. It cannot establish model fidelity, service quality or appropriate staffing merely by using the model's name.
What belongs in a case record?
The record should contain the information necessary and appropriate for the service, with clear access and retention practices. Common components include relevant registration details, assessments, plans, contacts, referrals, service updates, permissions, review decisions and transition or closure information.
Keep the person distinct from their participation in a program. A person may have several enrollments, goals and service episodes. A new enrollment should not overwrite an earlier one, and duplicate contacts should not create two conflicting histories.
Not all information belongs in every worker's view. Access to sensitive details should match the role and purpose. Shared coordination does not require indiscriminate sharing across every partner or reporting audience.
What is a case note?
A case note is a dated account of a relevant contact, observation or action. It should make clear what was reported, by whom, what the worker observed or assessed, what was agreed and what happens next. Separate facts, reported statements and interpretation.
For the Alex example, “reports childcare was unavailable” retains the source of the explanation. “Does not care about the program” adds an unsupported interpretation. The difference matters when someone later uses the notes to make a decision.
See case notes software for organizing and reviewing notes and client intake software for the front of the record.
Manage handoffs and workload
A useful handoff identifies the current goals, relevant context, actions already taken, unresolved questions and the next responsible person. A long file alone does not establish that the receiving worker understands the current situation.
High workloads can make documentation and review difficult. Address process, staffing, supervision and service constraints alongside technology. A summary can reduce reading effort, but it cannot create appointment capacity, available housing or a suitable referral.
Use caseload management software for workload visibility and case management best practices for the supporting habits. Avoid ranking people for attention through an unvalidated automated score.
How do you measure case management outcomes?
Start with the goals of the service and the person's relevant priorities. Distinguish activities, experience and outcomes: a referral made, the person's experience accessing it and a later change are different measures.
Where individual change is the question, comparable baseline and follow-up observations can help. Retain dates, definitions, instrument versions and missing follow-up. Other questions may use group-level or anonymous feedback. The method should fit the purpose.
Fictional reporting example. Of 50 enrolled participants, 40 receive a planned follow-up and 24 report progress on a defined goal. That is 60% of those followed up and 48% of the enrolled group with a recorded report of progress. Ten have no follow-up. Do not count them automatically as either successes or failures.
These results describe reported progress; they do not isolate the causal effect of case management. A program-wide claim may require additional evidence and an appropriate evaluation design. The outcome evaluation guide explains the distinction.
Compare across sites without imposing one assessment everywhere
A single-location program may share one instrument. A network of schools, service sites or partners may need local assessments and questions. Define the small shared core needed for valid comparisons, then map local fields to a common data dictionary.
Relevant registration context can be collected once and updated deliberately. Later observations retain their dates and program context. Shared measures need compatible definitions, units, populations and periods; identical labels alone do not create comparability.
Allow locally meaningful questions and keep incompatible measures separate. A common outcome heading should not erase the differences between programs or between individual goals. If a definition changes, document how the earlier and later results can—or cannot—be compared.
Case management, tracking, CRM and care management
Scroll horizontally to see all columns →
| Term | Useful distinction |
|---|---|
| Case management | The collaborative practice of assessment, planning, coordination and review |
| Case tracking | Visibility into status, tasks and events; one part of the broader practice |
| Case management system | Software that supports relevant records and workflows |
| CRM | A relationship-record platform whose capabilities and configuration may or may not fit case work |
| Care management | A related term often used in health settings; scope and responsibilities vary |
Some CRM and established case platforms include sophisticated workflows and analysis. Evaluate actual capabilities and configuration rather than assuming a product category only stores notes. The case management CRM guide considers that choice.
Where AI can help—and what remains a human responsibility
AI can assist with drafting summaries, applying a reviewed set of themes and locating relevant material. Useful output retains the source and date so an authorized worker can inspect what supports a statement and what may be missing.
In the Alex example, a suggested theme of “reported childcare barrier” could help a reviewer find related notes. It should not independently diagnose Alex, raise a safeguarding level or decide service priority. An automated summary can omit context or misinterpret language even when it includes a quotation.
Urgent concerns require the service's established human processes. Do not depend on an unvalidated model to detect every risk, and do not wait for an automated review when professional action is needed. The value of assistance is reduced administrative effort with appropriate review, not replacement of responsibility.
How Sopact supports connected case evidence
Sopact's approach connects collection, quantitative context and qualitative evidence around relevant records. A team can define the questions and analytical categories it needs, review findings against the source material and keep later observations connected to the appropriate program or person.
For codebook-based analysis, automated processing can apply the team's reviewed definitions across eligible notes or responses and support reruns after revisions. The team remains responsible for judging interpretation, coverage, access and the suitability of the method. The system's findings are inputs to review.
The practical ownership question is how much recurring work can be removed from applying codes, joining records and assembling reports. Include configuration, review and maintenance in the estimate. The qualitative and quantitative analysis guide gives a visual workflow and an illustrative staff-hours model.
Where an existing case system remains authoritative, verify the proposed integration, source ownership, permissions and correction process. Do not assume that a general platform description establishes the controls required for every clinical, public-service or sensitive setting.
Choose a manageable next step
Take one typical service journey and trace what happens from intake to the next review. Check whether the person and workers can understand the current plan, whether information is repeated unnecessarily and whether the next action has an owner.
Then review one report: can the team explain the result, denominator, source and unknowns without reconstructing the entire file? Improving that connection is a practical starting point for both service continuity and reporting.
Continue with the Case Intelligence course. For reporting, use How to Write an Impact Report and report examples.
Watch: connect collection with context
This introduction explains the collection and analysis workflow. It is not clinical practice guidance or validation of an automated risk assessment.
Frequently asked questions
What is case management in simple terms?
It is coordinated work with a person or family to understand needs, agree goals, connect support and review progress. Relationships, judgment and appropriate documentation work together.
Are the six stages always followed in order?
No. They are a useful explanatory structure. Assessment, planning and review can overlap or repeat, and the actual process depends on the service and situation.
Does case closure mean every goal was achieved?
No. Closure or transfer can happen for different reasons. Record the reason, current status, unresolved needs and relevant next arrangements rather than treating closure as automatic success.
Is a case manager the same as a social worker?
Not necessarily. Roles, qualifications and titles vary across settings. Some social workers provide case management, but the title case manager alone does not establish a particular professional qualification.
Can AI replace a case manager?
No. AI can assist with certain administrative and analytical tasks. The relationship, assessment, service decisions and professional responsibilities remain with appropriately qualified people.
Can different sites use different forms?
Yes. Agree the shared definitions needed for valid comparison, map local collection to them and retain local questions where useful. Keep incompatible measures separate.
What is case intelligence?
In this context it means making connected case information useful for reviewed decisions: relevant history, quantitative context, source evidence and changes over time. It should not mean unverified automated judgment about a person.
